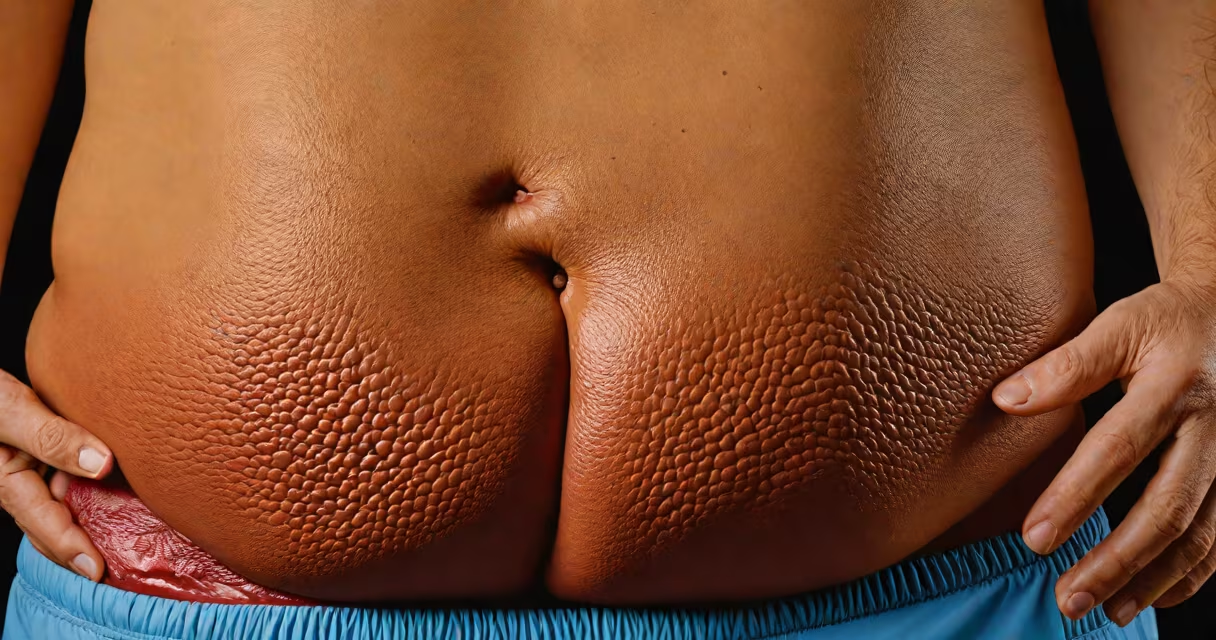
Liver damage can cause bloating through fluid retention, impaired digestion, and increased pressure in the portal vein system. This occurs when scar tissue reduces blood flow through the liver, leading to ascites-fluid buildup in the abdomen-and abdominal swelling.
Bloating from liver disease is not just discomfort-it's a sign of underlying dysfunction. The liver processes nutrients, detoxifies blood, and produces proteins that regulate fluid balance. When damaged, especially in advanced stages like cirrhosis, these functions fail. Fluid leaks into the abdominal cavity, causing visible and palpable bloating. This is distinct from gas-related bloating, which resolves quickly and lacks associated symptoms like leg swelling or fatigue.
A 2021 study published in Journal of Hepatology found that 60% of patients with compensated cirrhosis reported abdominal distension, with 35% developing clinically significant ascites within five years. The condition progresses silently-early signs like mild bloating are often dismissed until complications arise.
The liver sits beneath the diaphragm and filters blood from the intestines via the portal vein. When scar tissue forms-common in alcohol-related liver disease, hepatitis B or C, or fatty liver disease-the liver becomes stiff and less able to handle blood flow. This increases pressure in the portal vein, known as portal hypertension.
High pressure forces fluid out of blood vessels and into the abdominal space. The liver also fails to produce enough albumin, a protein that keeps fluid in the bloodstream. Low albumin levels allow fluid to leak into tissues. Together, these mechanisms cause ascites-a sign of advanced liver disease.
Damaged livers struggle to metabolize hormones and process digestive enzymes. Reduced bile production impairs fat breakdown, leading to malabsorption and gas buildup. This contributes to bloating that feels different from typical gas-persistent, tight, and worsening over days.
Bloating from liver issues differs from functional gastrointestinal bloating. It's characterized by volume increase, not just gas. The following table outlines key differences:
| Feature | Liver-Related Bloating | Gas-Related Bloating |
|---|---|---|
| Onset | Gradual, over weeks | Sudden, after meals |
| Duration | Persistent, doesn't resolve with passing gas | Resolves in minutes to hours |
| Accompanying signs | Abdominal swelling, weight gain, leg edema, jaundice | Flatulence, belching, cramping |
| Response to diet | Minimal improvement with low-FODMAP or gas-reducing diets | Clear relief with dietary changes |
Ascites-fluid accumulation in the abdomen-is the most serious form. It can reach 10 liters or more. A 2019 report from the American Association for the Study of Liver Diseases (AASLD) states that ascites develops in 50% of patients with decompensated cirrhosis and is linked to a 5-year survival rate below 50% without treatment.
Many assume bloating is always due to diet, gas, or constipation. But persistent bloating with weight gain, swollen legs, or yellowing skin (jaundice) signals systemic illness. One patient I saw had bloating for six months, attributed to "eating too much," until an ultrasound revealed 5 liters of fluid in the abdomen. He was diagnosed with alcoholic cirrhosis.
Another confusion: bloating from liver disease is not relieved by laxatives or antacids. These treat gut-based causes. Liver-related bloating requires medical intervention-diuretics, paracentesis (fluid removal), or even liver transplant in severe cases.
Some believe bloating equals "bad digestion." But in liver disease, the issue is not poor digestion-it's organ failure. The liver isn't breaking down food; it's failing to maintain fluid balance and detoxify blood. This distinction is critical for proper diagnosis.
Bloating from liver damage rarely resolves on its own. Red flags include:
If you have risk factors-chronic alcohol use, viral hepatitis, obesity, or family history of liver disease-bloating should prompt evaluation. A physical exam, ultrasound, and blood tests (like ALT, AST, bilirubin, and albumin) can confirm liver involvement.
For example, a 54-year-old man with a 20-year history of heavy drinking presented with bloating and fatigue. His labs showed elevated AST (120 U/L), low albumin (2.8 g/dL), and normal kidney function. An ultrasound confirmed ascites and nodular liver texture. He was diagnosed with alcoholic cirrhosis and started on spironolactone and furosemide to reduce fluid.
Doctors use imaging and lab work to distinguish liver-related bloating from other causes. Ultrasound detects fluid and assesses liver texture. CT scans show scarring and portal vein enlargement. Blood tests measure liver enzyme levels and clotting ability.
Treatment focuses on reducing fluid and managing the underlying cause. Diuretics like spironolactone and furosemide are first-line. For large-volume ascites, paracentesis removes up to 5 liters of fluid in one session. In refractory cases, transjugular intrahepatic portosystemic shunt (TIPS) surgery reduces portal pressure.
Addressing the root cause is essential. Alcohol cessation, antiviral therapy for hepatitis B/C, or weight management for fatty liver disease can slow progression. Patients with advanced disease may need a liver transplant.
Early detection improves outcomes. The European Association for the Study of the Liver (EASL) recommends screening high-risk individuals annually with elastography or FibroScan to detect fibrosis before cirrhosis develops.