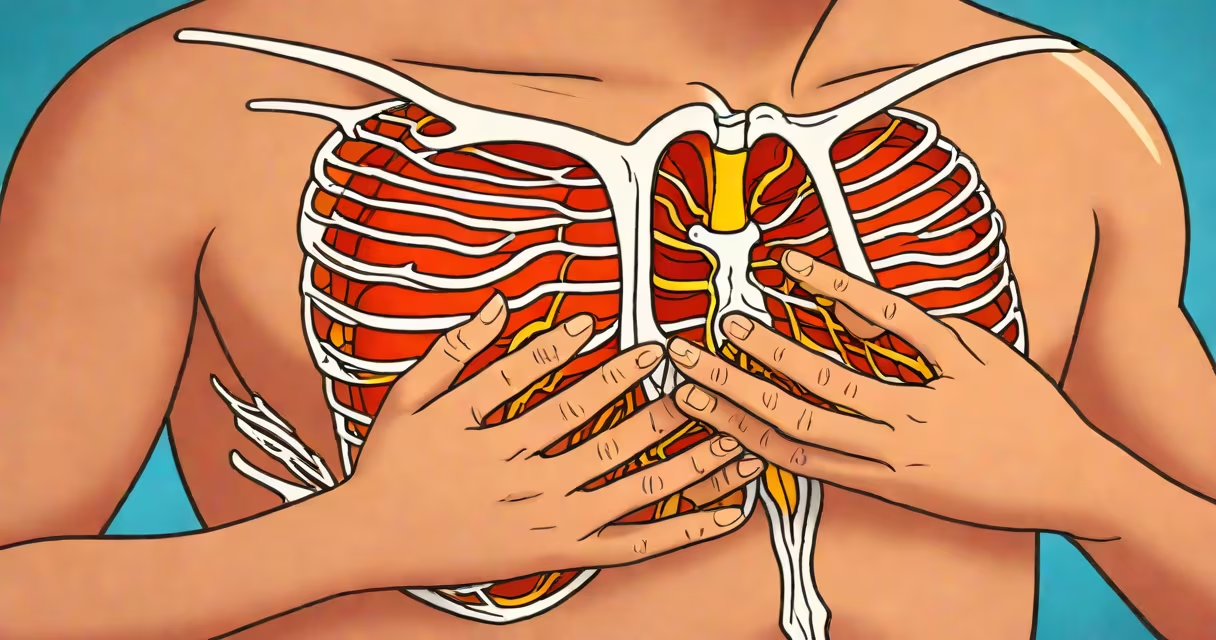
Costochondritis is inflammation of the cartilage connecting the ribs to the breastbone, causing sharp, localized chest pain that worsens with movement or pressure. It's a common cause of non-cardiac chest pain, especially in adults under 50.
The condition typically presents as a stabbing or aching pain in the front of the chest, most often on the left side. Pain may radiate to the arm or shoulder but rarely spreads to the jaw or neck, which helps distinguish it from cardiac events. Symptoms often develop suddenly and can last weeks to months, though they usually resolve without long-term complications.
According to the American College of Rheumatology, costochondritis accounts for up to 15% of non-heart-related chest pain cases seen in primary care. It's frequently misdiagnosed due to overlapping symptoms with heart disease, panic attacks, or gastrointestinal reflux. A physical exam revealing tenderness at the costosternal joints-where the ribs meet the sternum-is key to diagnosis.
Costochondritis results from inflammation in the costosternal joints, where the upper ribs attach to the sternum via cartilage. This cartilage is rich in blood vessels and nerves, making it sensitive to irritation. The exact trigger is often unknown, but potential causes include minor trauma, repetitive strain, viral infections, or autoimmune responses.
Repetitive movements such as heavy lifting, coughing, or intense exercise can strain the joint area. In one study published in *The Journal of Rheumatology*, 30% of patients reported recent upper respiratory infections prior to symptom onset. Others describe pain following a fall or sudden twisting motion.
Unlike heart-related chest pain, costochondritis pain doesn't change with exertion or rest. It remains constant unless pressure is applied. The pain may fluctuate in intensity but rarely worsens during physical activity-another clue distinguishing it from angina.
Primary symptoms include:
Some patients report pain that shifts between sides or mimics heartburn. However, costochondritis does not cause shortness of breath, dizziness, or sweating-symptoms associated with heart attacks. If any of these appear, seek immediate medical evaluation.
A non-obvious distinction: costochondritis pain is typically reproducible. Pressing firmly on the joint reproduces the discomfort. This physical sign is more reliable than imaging for early diagnosis. X-rays and CT scans generally show no abnormalities, reinforcing the need for clinical assessment.
While costochondritis is a single condition, subtypes exist based on onset and underlying cause:
| Type | Onset | Common Triggers | Typical Duration |
|---|---|---|---|
| Acute | Sudden | Physical strain, injury, viral infection | Days to weeks |
| Chronic | Gradual | Autoimmune conditions, repetitive stress | Months to years |
| Recurrent | Episodic | Stress, cold weather, poor posture | Variable |
Chronic cases are less common but may indicate an underlying issue like rheumatoid arthritis or ankylosing spondylitis. These conditions affect connective tissues and can lead to persistent joint inflammation. If pain recurs frequently or spreads beyond the chest wall, further testing may be needed.
Doctors rule out heart and lung problems first. An electrocardiogram (ECG) and blood tests may be ordered to exclude myocardial infarction or pulmonary embolism. Imaging is rarely needed unless the pain is atypical or unresponsive to treatment.
Costochondritis is often confused with Tietze's syndrome-a similar condition involving swelling and pain in the same joints. The key difference: Tietze's includes visible swelling, while costochondritis does not. Swelling suggests a different inflammatory process and may require different management.
I once evaluated a patient who described "stabbing pain" in her left chest after a weekend of gardening. She had no history of heart disease, and her ECG was normal. Pressing on the third rib-cartilage junction reproduced the pain. After ruling out cardiac causes, the diagnosis was confirmed clinically. She responded well to NSAIDs and rest within two weeks.
Most cases improve with conservative measures. Treatment focuses on reducing inflammation and managing pain. Over-the-counter NSAIDs like ibuprofen or naproxen are first-line therapy. They reduce both pain and swelling when taken consistently for 3-5 days.
Local heat or ice application can provide temporary relief. Avoiding activities that aggravate the area-such as heavy lifting or stretching-helps prevent flare-ups. Physical therapy may be recommended for chronic cases, especially if posture or muscle imbalances contribute to strain.
In rare instances, corticosteroid injections into the joint may be used. A 2021 review in *Pain Medicine* found that injection therapy led to significant pain reduction in 68% of patients after four weeks, though effects were not sustained beyond six months in many.
For those seeking alternatives, acupuncture and gentle stretching have shown modest benefit in small trials. However, evidence remains limited compared to pharmacological options.
Chest pain from costochondritis is often mistaken for heart attack, panic disorder, or acid reflux. Here's how to tell them apart:
When in doubt, consult a healthcare provider. Misdiagnosis delays proper care and increases unnecessary testing.
Costochondritis symptoms and treatment are manageable with clear diagnostic steps and targeted interventions. Early recognition prevents prolonged suffering and reduces healthcare costs. Most cases resolve without surgery or long-term medication.