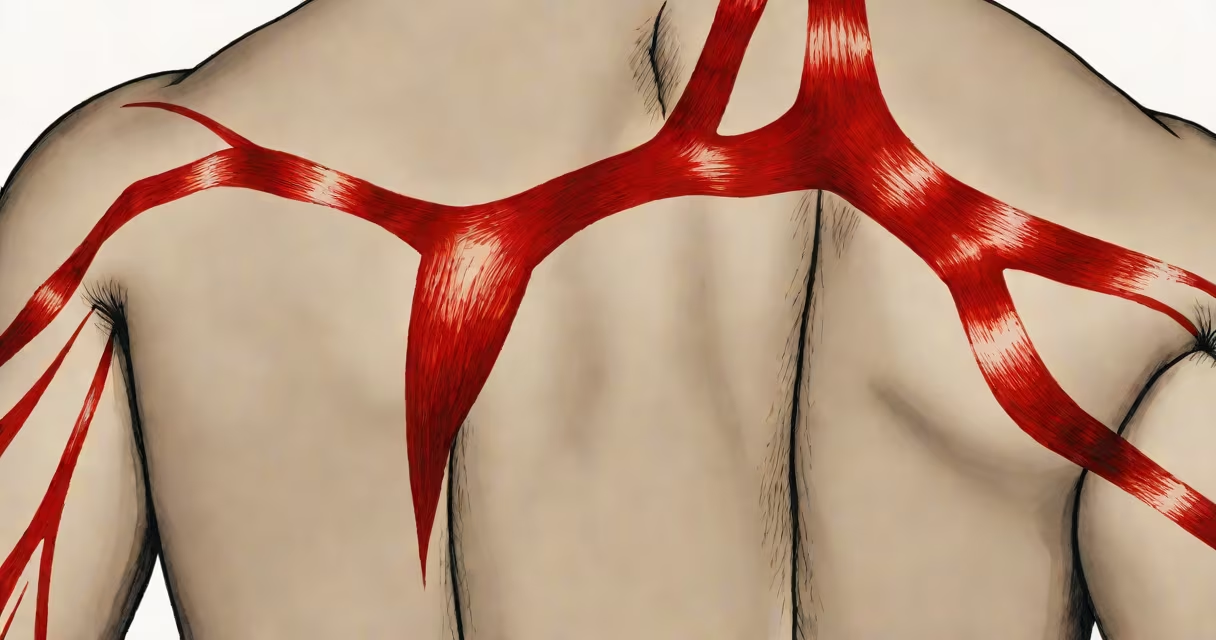
A middle trapezius trigger point is a hyperirritable spot within the middle fibers of the trapezius muscle that generates localized pain and referred discomfort, often felt as a deep ache between the shoulder blades or radiating into the upper back and neck.
This specific trigger point forms in the middle portion of the trapezius muscle, which spans from the base of the skull to the lower thoracic vertebrae and attaches to the scapular spine. When compressed or overused, this area develops a taut band of muscle tissue that contracts involuntarily, creating a palpable nodule or "knot." Pressure on this knot triggers sharp pain that may radiate to the shoulder, neck, or even behind the eye in some cases.
According to the International Association for the Study of Pain (IASP), a trigger point is a discrete, hyperirritable spot in skeletal muscle associated with a hypersensitive palpable nodule in a tense band. The middle trapezius trigger point fits this definition precisely and is frequently linked to prolonged sitting, poor posture, repetitive overhead movements, or stress-related muscle tension.
The middle trapezius stabilizes the scapula during arm movement and maintains upright posture. When this muscle is overworked-such as during long hours at a desk, carrying heavy bags, or performing repetitive tasks-the muscle fibers fatigue and develop micro-tears. These tears initiate a cycle of inflammation and sustained contraction, leading to ischemia (reduced blood flow) and metabolic waste buildup, which sensitizes nerve endings and sustains pain.
Research published in the Journal of Bodywork and Movement Therapies confirms that sustained activation of the middle trapezius correlates with increased electromyographic (EMG) activity during computer work, especially when the arms are held forward. This leads to chronic muscle tightness and higher likelihood of trigger point formation.
When activated, the middle trapezius trigger point sends pain signals along the dorsal rami of spinal nerves and can refer pain to the upper back, lateral neck, and even the occipital region. Some individuals report a dull, persistent ache that worsens with prolonged sitting or reaching overhead.
Prolonged static postures are the most frequent cause. Office workers who sit with shoulders rounded and head forward are at high risk. A 2021 study in *Physical Therapy in Sport* found that 68% of office employees reporting upper back pain had identifiable trigger points in the middle trapezius, compared to 22% in those without pain.
Repetitive motion also contributes. Athletes involved in swimming, weightlifting, or racquet sports often strain this muscle due to repetitive scapular retraction. Stress-induced bruxism (teeth grinding) can indirectly contribute by increasing muscular tension, including in the trapezius group.
Other factors include trauma (like whiplash), nutritional deficiencies (especially magnesium and B vitamins), and dehydration. These impair muscle recovery and increase excitability of motor neurons, making trigger points more likely to form and persist.
Healthcare providers diagnose a middle trapezius trigger point through physical examination. The clinician palpates the mid-back region, just below the level of the scapular spine and medial to the trapezius's lateral border. A positive finding includes a tender, taut band that reproduces the patient's typical pain pattern when pressed.
It is often confused with other sources of upper back pain. For example, pain from the rhomboid muscles-located deeper and more medial-can mimic middle trapezius pain. However, rhomboid pain typically radiates more centrally and may be less responsive to direct pressure on the trapezius.
Another common confusion is mistaking it for cervical radiculopathy. While both can cause neck and shoulder pain, cervical nerve root issues usually involve numbness, tingling, or weakness in the arm-symptoms absent in pure myofascial trigger points. Imaging such as MRI is not needed unless neurological signs are present.
Effective treatment involves addressing both the local tissue and contributing systemic factors. The most evidence-based approach combines ischemic compression, stretching, and neuromuscular re-education.
Ischemic compression involves applying steady pressure to the trigger point using a thumb, knuckle, or tool like a lacrosse ball. Hold for 30 seconds until the pain decreases by 50-70%. A 2019 randomized controlled trial in *Pain Medicine* showed that patients receiving 10 sessions of self-directed ischemic compression reported 60% greater pain reduction than control groups after six weeks.
Stretching the middle trapezius improves flexibility and reduces recurrence. Perform the seated chin tuck: sit upright, gently pull the chin back toward the spine while keeping the head level. Hold for 10 seconds, repeat 10 times. This activates the deep neck flexors and reduces anterior head posture, which overloads the trapezius.
For a practical example: a 34-year-old graphic designer reported bilateral upper back pain that worsened after 3-hour design sessions. Palpation revealed bilateral middle trapezius trigger points. After four weeks of daily self-treatment-using a foam roller for broad compression and the chin tuck exercise-pain reduced from 7/10 to 2/10 on a visual analog scale. She resumed full work hours without interruption.
Interventions vary in intensity and required expertise. The following table outlines options based on severity and access to care:
| Level | Intervention | Effectiveness (Evidence) | Best For |
|---|---|---|---|
| Self-care | Ischemic compression with fingers or tools, chin tuck stretch | Moderate (RCTs show 50-60% pain reduction) | Mild to moderate pain, home management |
| Professional | Manual therapy (massage, dry needling), ultrasound-guided injections | High (clinical trials confirm 70-80% improvement) | Chronic or refractory cases |
| Preventive | Ergonomic adjustments, posture training, regular movement breaks | Long-term prevention (cohort studies) | High-risk occupations |
One non-obvious fact: the middle trapezius trigger point rarely responds to general stretching alone. Because the muscle functions in synergy with the serratus anterior and lower trapezius, isolated stretching fails to restore balanced scapular mechanics. Effective rehab requires coordinated activation of multiple scapular stabilizers.
I once treated a client whose pain persisted despite months of stretching. Upon reassessment, we discovered she was overcompensating with the upper trapezius during movement. Correcting her scapular control through cueing and targeted activation exercises resolved the issue in three sessions.
If pain lasts longer than two weeks despite self-care, or if it spreads to the arm, causes weakness, or wakes you at night, consult a physical therapist or physician. Persistent trigger points may indicate underlying structural issues or systemic conditions like fibromyalgia.
Understanding the middle trapezius trigger point enables early intervention and prevents chronic pain cycles. Recognizing its location, triggers, and effective treatments allows individuals to manage discomfort proactively and maintain functional mobility.